STATEN ISLAND WHAT IS SPEECH THERAPY PRONUNCIATION ENUNCIATION ARTICULATION THERAPY?
SPEECH THERAPY PRONUNCIATION ENUNCIATION ARTICULATION THERAPY IN STATEN ISLAND

As Featured In:







Speech Therapists Travel to Your Staten Island Home! | Top In-Person and Remote Private Pay Speech Therapy Pronunciation, Enunciation Articulation in Staten Island | Free Consultation and Meet & Greets With Our Professionals
Speech Therapists Travel to Your Staten Island Home! | Top In-Person and Remote Private Pay Speech Therapy Pronunciation, Enunciation Articulation in Staten Island | Free Consultation and Meet & Greets With Our Professionals
We work with children, teens, and adults. Many teens still struggle with pronunciation and speech clarity (e.g., R, S, Z, L, and TH sounds), as well as speaking confidence for school presentations, social interactions, and everyday communication. Our therapists support teens with articulation, clear speech, pacing, and effective communication skills. We travel to Annadale, Arden Heights, Arlington, Arrochaar, Bay Terrace, Bloomfield, Brighton Heights, Bulls Head, Castleton Corners, Charleston, Chelsea, Clifton, Concord, Dongan Hills, Egbertville, Elm Park, Eltingville, Emerson Hill, Fort Wadsworth, Graniteville, Grant City, Grasmere, Great Kills, Greenridge, Grymes Hill, Hamilton Park, Heartland Village, Huguenot, Lighthouse Hill, Livingston, Manor Heights, Jefferson, Mariners Harbor, Meiers Corners, Midland Beach, New Brighton, New Dorp, New Springville, Oakwood, Old Place, Old Town, Pleasant Plains, Port Ivory, Port Richmond, Prince’s Bay, Randall Manor, Richmond Valley, Richmondtown, Rosebank, Rossville, Saint George, Sandy Ground, Shore Acres, Silver Lake, South Beach, Stapleton, Stapleton Heights, Sunnyside, Todt Hill, Tompkinsville, Tottenville, Tottenville Beach, Travis, Ward Hill, West New Brighton, Westerleigh, Willowbrook, and Woodrow.
Our Speech-Language Pathologists and Therapists
We travel to you and we also offer remote services. Some of our speech-language pathologists are trained in the Orton Gillingham approach. Many of our speech-language pathologists are trained in literacy and offer support with decoding, spelling and reading fluency services. Our speech-language pathologists and therapists work with babies, toddlers, school-age students, and adults with expertise in:
Our Speech Language Pathologists & Therapists
We travel to you and we also offer remote services. Some of our speech-language pathologists are trained in the Orton Gillingham approach. Many of our speech-language pathologists are trained in literacy and offer support with decoding, spelling and reading fluency services. Our speech-language pathologists and therapists work with babies, toddlers, school-age students, and adults with expertise in:
- Pronunciation/Enunciation
- Articulation
- Expressive Language Disorder
- Writing & Speaking Therapy
- Comprehension- Listening & Reading
- Listening Comprehension
- Auditory Processing
- Vocabulary
- Teens – Language Therapy
- Stuttering
- Feeding
- Oral Motor
- Voice
- AAC
- Adult Speech Therapy
- Public Speaking
- Accent Reduction Modification Speech Therapy
Training/Certifications












Staten Island Letters is owned and operated by Brooklyn Letters.
A Few Terms to Understand
Chronological Age – The child’s actual age (for example: 12 months, 3 years).
Linguistic Age – Refers to how the child’s vocabulary, grammar, and social use of words compare to peers. For example, a child might have a chronological age of 3:3, but his or her expressive language skills could be at the 2:9 level, indicating a six-month gap. This six-month gap indicates that his or her speech production skills should be at the 2:9 level, not the 3:3 year mark. Determining this gap, if there is one, is imperative when evaluating for speech sound disorders.
What are Speech Sound Disorders?
As children develop their language skills, they learn to produce sounds. Most children say /p/, /m/, and /w/ early on, while sounds like /r/, /l/, or “th” often take longer to master. By four years old, children can produce and say the majority of speech sounds correctly.
When a child is having difficulties with a sound that should have been mastered based on the child’s chronological and linguistic ages, it might be an indication of a speech sound disorder which can affect their communication skills. This may either be an articulation disorder or a phonological disorder.
For parents seeking clarity on communication milestones and intervention, we offer a helpful guide into what an early language assessment is, how a speech pathologist evaluates children, the role of play in understanding communication, and when you should consider professional early intervention.
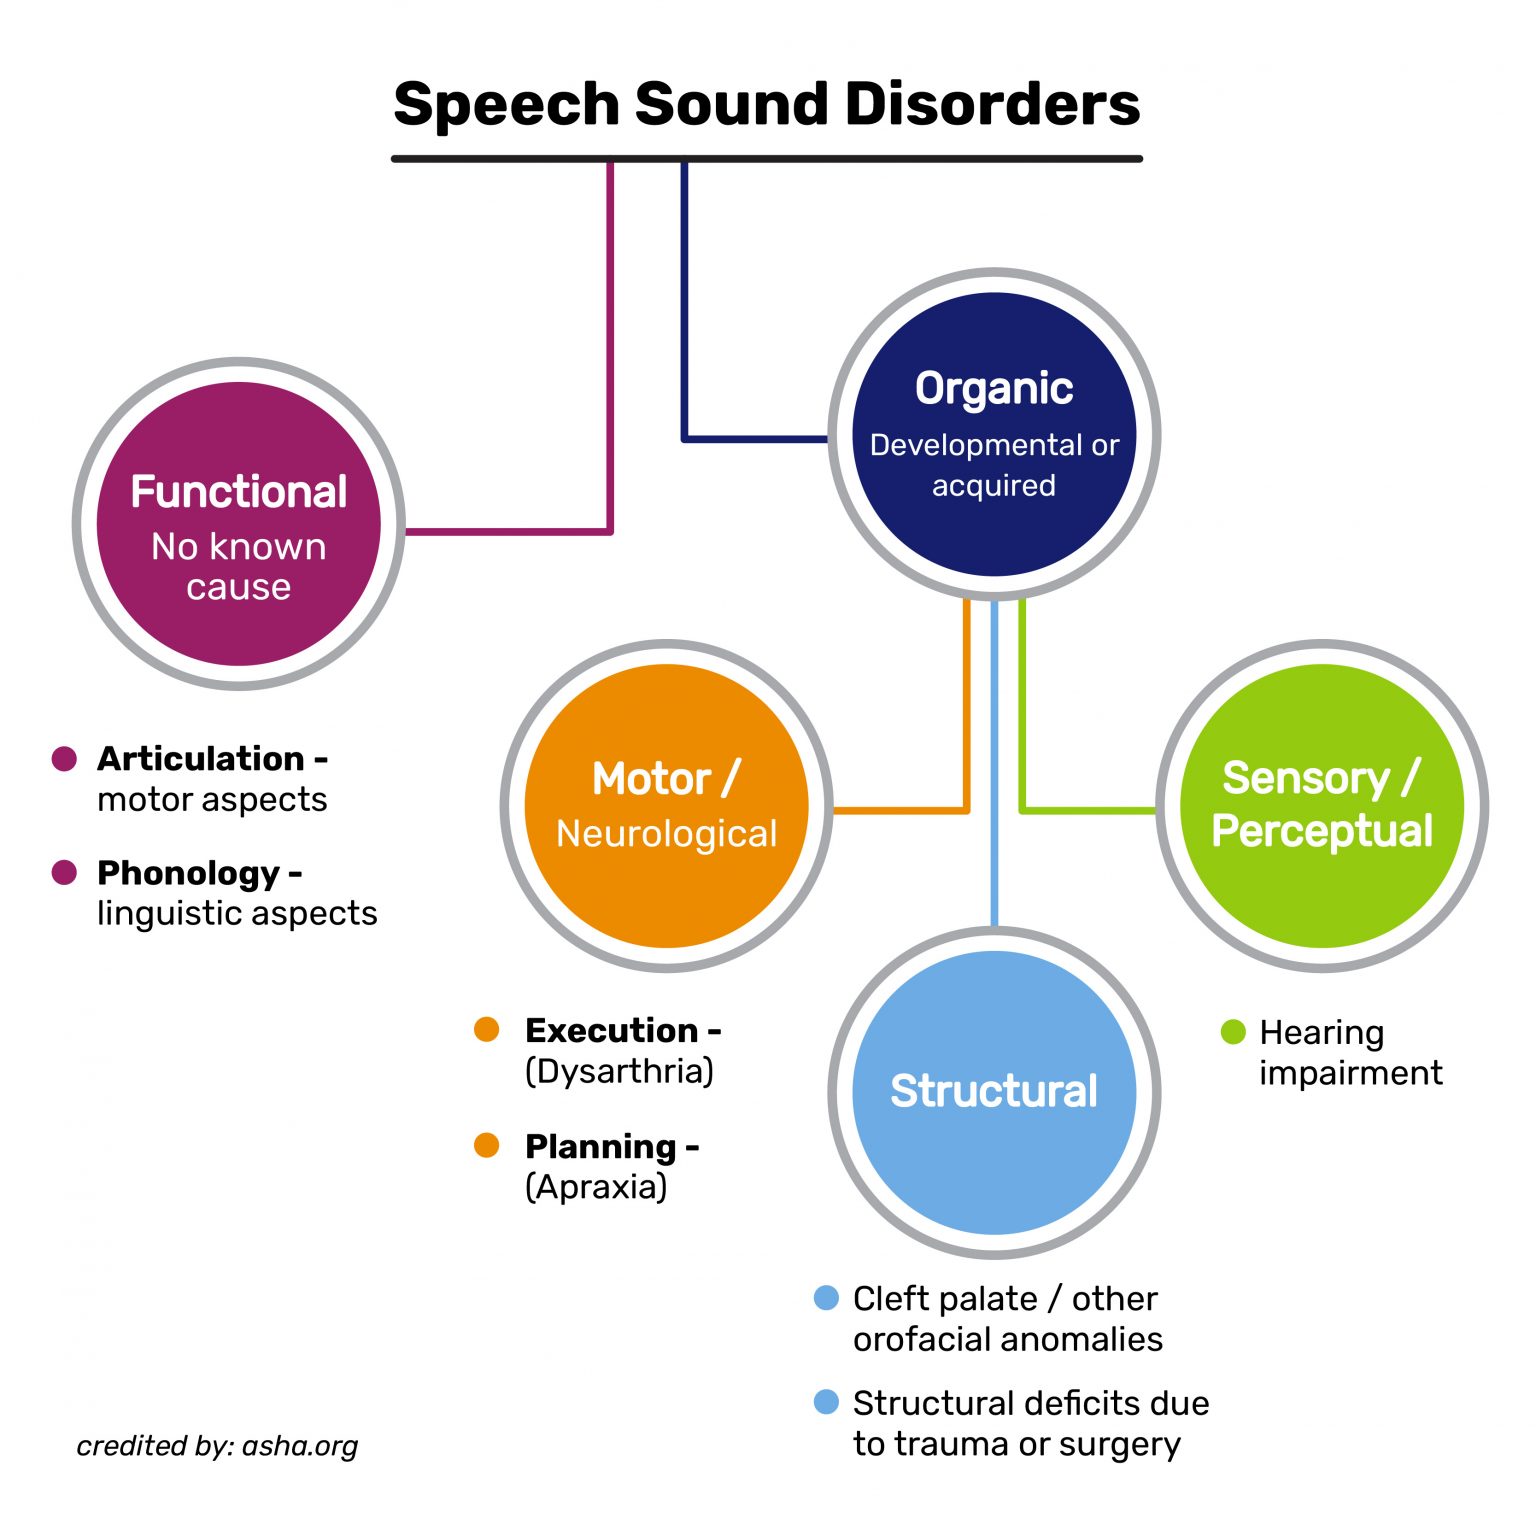
What are the Most Common Speech Sound Disorders?
Articulation Disorder – This affects children’s speech articulation on a phonetic and motoric level, which means they have trouble saying individual speech sounds, e.g. consonants and vowels. For example, when a child cannot produce the /l/ sound, when he or she should be able to produce it based on the chronological and linguistic ages, and does not show a systematic error pattern (see below for phonological disorder), one can then assume that it is an articulation disorder.
Phonological Disorder – This disorder occurs at the phonemic/linguistic/cognitive levels (a level higher than the phonetic/motoric aspects of speech production. Children with a phonological disorder show systematic patterns with their speech production errors, e.g. unclear speech, consistently deleting /m/ in initial sounds, by saying “at” for “mat” or “ad” for “mad” for CVC (consonant-vowel-consonant) words, when the age error is unexpected for the child’s chronological and linguistic ages.
Lisps – Lisps are a type of speech sound error where a child has difficulty producing the /s/ and /z/ sounds correctly. The most common types are interdental lisps (where the tongue protrudes between the teeth, producing a “th” sound for /s/ or /z/), lateral lisps (where air escapes over the sides of the tongue), and dentalized lisps (where the tongue presses against the front teeth). While some lisps may be developmental and resolve on their own, others may require speech therapy if they persist past the expected age of development.
Other sounds disorders are dysarthria and apraxia of speech (childhood apraxia speech assessment and childhood apraxia of speech treatment), which are significantly more uncommon speech sound disorders compared to articulation and phonological disorders. Here is everything you want to know about treatment approaches for speech sound disorders.
How to Tell if a Child has Articulation Difficulties?
A child with articulation issues may:
- Become excessively frustrated when communicating with others.
- Producing speech that is difficult to understand, even for familiar listeners.
- When learning certain words, tend to use only vowel sounds (very open-mouthed noises).
- Produces speech that is less clear than other children of the same age.
- Produce an interdental lisp (e.g., tongue protruding between the teeth when saying a /s/ or /z/ sound) if over the ages of 3.5 – 4 years.
- Be school-aged and still having difficulty with producing clear sounds. The last sounds to develop are voice and voice-less “th.”
PBS.Org Average Number of Words Produced
- At 15 months= 14 words
- 18 months= 68 words
- 23 months= 200 words
- 24 months- 200 to 300 words Dr. Rhea Paul, Ph. D.
- 30 months= 570 words
PBS.Org Average Number of Words Produced
- At 15 months= 14 words
- 18 months= 68 words
- 23 months= 200 words
- 24 months- 200 to 300 words Dr. Rhea Paul, Ph. D.
- 30 months= 570 words
Foundational Skills to Build Articulation
- Attention and concentration: Sustained effort, listening and doing activities without distraction and being able to hold that effort long enough to get the task done (e.g., being able to attend to speech and sounds long enough to be able to process the information).
- Hearing: For detection of speech sounds.
- Good middle ear functioning most of the time (e.g., a child with ongoing ear infections, ‘glue ear’ or colds which block the ears may have fluctuating hearing levels which can affect speech).
- Process speech sounds, identify and hear differences between sounds.
- Discriminating sounds
WARNING!
Despite being uncommon in children, many speech pathologists misdiagnose children’s speech production errors due to the lack of understanding between phonology, morphology/syntax, and speech production skills. Many speech pathologists we work with focus only on the motoric aspects of speech production. The reason for this divide in the field of speech language pathology is because there is variability in training at the Masters and Post-Masters Degree levels. Likewise, there is growing pressure placed on speech pathologists, particularly private clinicians, to use commercialized products that are not backed up by research. Many parents ask for these products and commercialized programs because that is what they have been told to do.
What Causes Speech Sound Disorders?
Speech sound disorders can also occur in adults, which typically start from childhood or after a stroke or traumatic brain injury. However, they are the most common when children learn speech sounds and cannot produce the correct speech production sounds on their own. Most of the time we do not know what causes speech sound disorders. Speech production is simply something we take for granted. Most of the children who utilize our services cannot master certain sounds on their own, so they need a boost in how to correctly enunciate these sounds. This is how we can help your child!
Other possible causes of speech sound disorders in children include:
- most of the time it’s unknown;
- autism and other developmental disorders;
- genetic syndromes, such as Down syndrome;
- hearing loss (from ear infections or other causes); and,
- brain damage caused by injuries or conditions like cerebral palsy.
Techniques to Treat Speech Sound Disorders
In addressing speech sound disorders, it is crucial to test a child for hearing loss as it can interfere with speech skills and language development. Just because a child detects sounds, it does not mean they are processing these sounds. Pediatricians do not perform full audiological evaluations. An audiologist must rule out any hearing issues, such as undetected ear infections, which can negatively impact speech skills and language development. We have worked with many children who had undetected hearing issues and surprised their parents when their hearing test uncovered hearing loss (most of the time it is temporary hearing loss and easily treatable).
Toddlers:
Speech sound development is strongly tied to the child’s expressive language abilities and toddlers who are hard to understand can be unintelligible for many reasons. A delay in expressive vocabulary and a delay in stringing words together is usually accompanied by a delay in the sound acquisition and decreased speech intelligibility. Therapy typically focuses on increasing the child’s expressive vocabulary and helping the child increase the complexity of what they say. As the child’s vocabulary expands, the number and variety of sounds increase and the toddler is more understood. For toddlers with a limited sound repertoire, we teach early developing sounds to start building the foundation for learning words. Some toddlers can pronounce words but they are hard to understand. They may need help acquiring early developing sounds and/or eliminating atypical sound errors. Some toddlers can say a lot of words and they are well understood, but they need help using their words in the right environment. Here, the therapy focuses on social language use.
Preschoolers:
Therapy may focus on increasing the child’s vocabulary and the complexity of what they say, facilitating their underlying speech development. Some preschoolers need help learning age-appropriate sounds and/or reducing speech error patterns, e.g., the child says tiss, for kiss, even though the child can say the k sound.
Speech Therapy for Teens (Articulation & Clarity):
Some teens continue to have difficulty with certain speech sounds or with speaking clearly in conversations, reading aloud, class discussions, presentations, or interviews. Teen speech therapy focuses on:
- Correcting later-developing sounds (e.g., R, L, S, Z, TH)
- Reducing fast or “mumbled” speech
- Improving enunciation and clarity in everyday conversation
- Building confidence for oral presentations and social communication
- Supporting self-advocacy and speaking skills in school environments
Therapy is adapted to be age-appropriate, respectful, and collaborative. Teens are active participants in setting goals so progress feels meaningful and relevant.
School Age:
For students who don’t have significant expressive language issue, speech therapy typically focuses on teaching later developing sounds, e.g. th, l, and r, reducing sound distortions, e.g., lisp, and resolving any remaining speech error pattern(s) not exhibited by peers.
A licensed speech-language pathologist can then help correct the child’s speech delay problems. The licensed speech-language pathologist will conduct a series of tests to check how the child says sounds at various levels, e.g. sound, syllable, word, sentence, etc., and in varying contexts in words, e.g. initial, medial, final, within clusters/blends, and more. We also check out the context of the child’s movements of their articulator’s: lips, jaw, and tongue placement in varying phonetic/linguistic contexts.
Likewise, it is crucial to test a child’s language skills to see if the speech problem is linked to a language disorder based on his or her linguistic age. This is a bit complicated to break down, but we can certainly explain this connection to you. As previously stated, many speech language pathologists we work with do not connect the speech production dots to language skills. Often, this leads them to misdiagnose and look too myopically at why a child is incorrectly producing sounds. Our assessments break down all systems so your child will have an accurate assessment. Assessments guide treatment, which will save you money.
ROARING WITH THE R SOUND
Mastering the Art of Correct Pronunciation
Speech Intelligibility
The term intelligibility refers to ‘speech clarity’ or the proportion of a speaker’s output that a listener can readily understand. In typical development, as children learn to talk, their comprehensibility to those around them steadily increases. A key characteristic of children with persistent speech errors is that they are often significantly less intelligible than non-speech-impaired children of the same age. Rhotacism is common in children because the “r” is one of the most challenging sounds to pronounce in English.
In young children there is often quite a marked difference between single word (SW) and conversational speech (CS) intelligibility; between intelligibility to their close family members and intelligibility to unfamiliar listeners; and intelligibility in known versus unknown conversational topics. With regard to families, siblings may sometimes be more adept than parents in comprehending what their little brothers and sisters are saying.
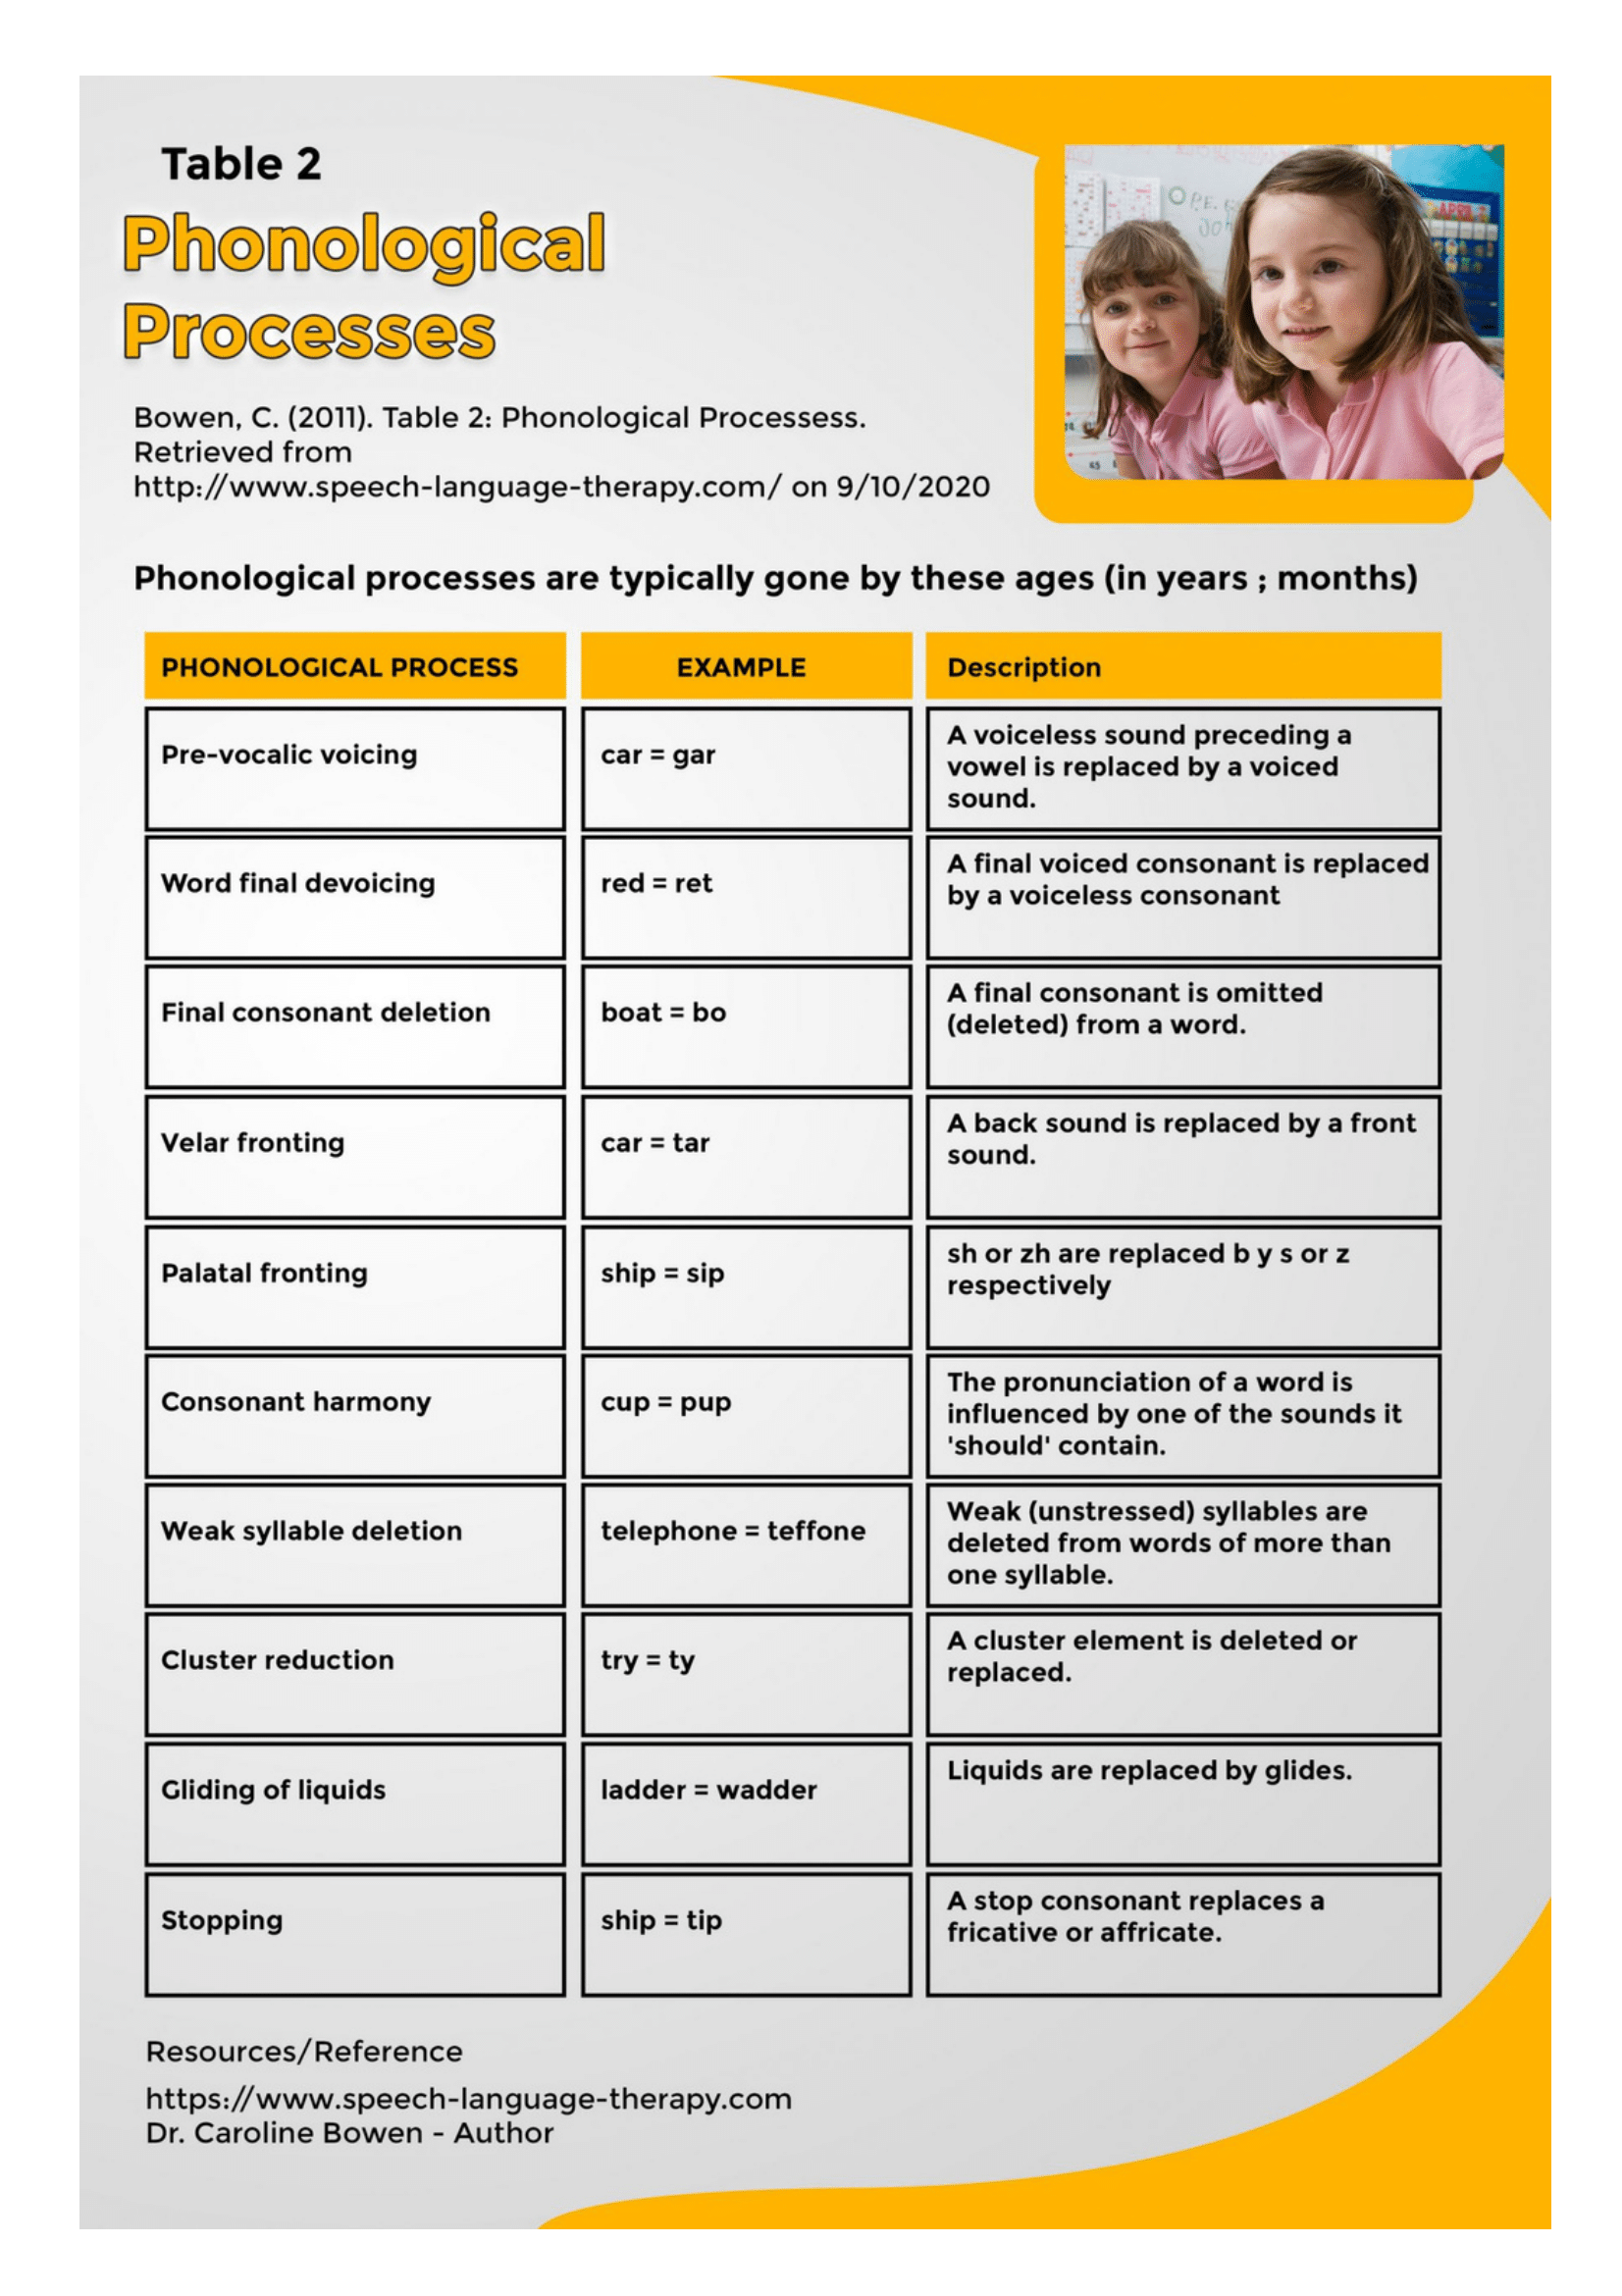
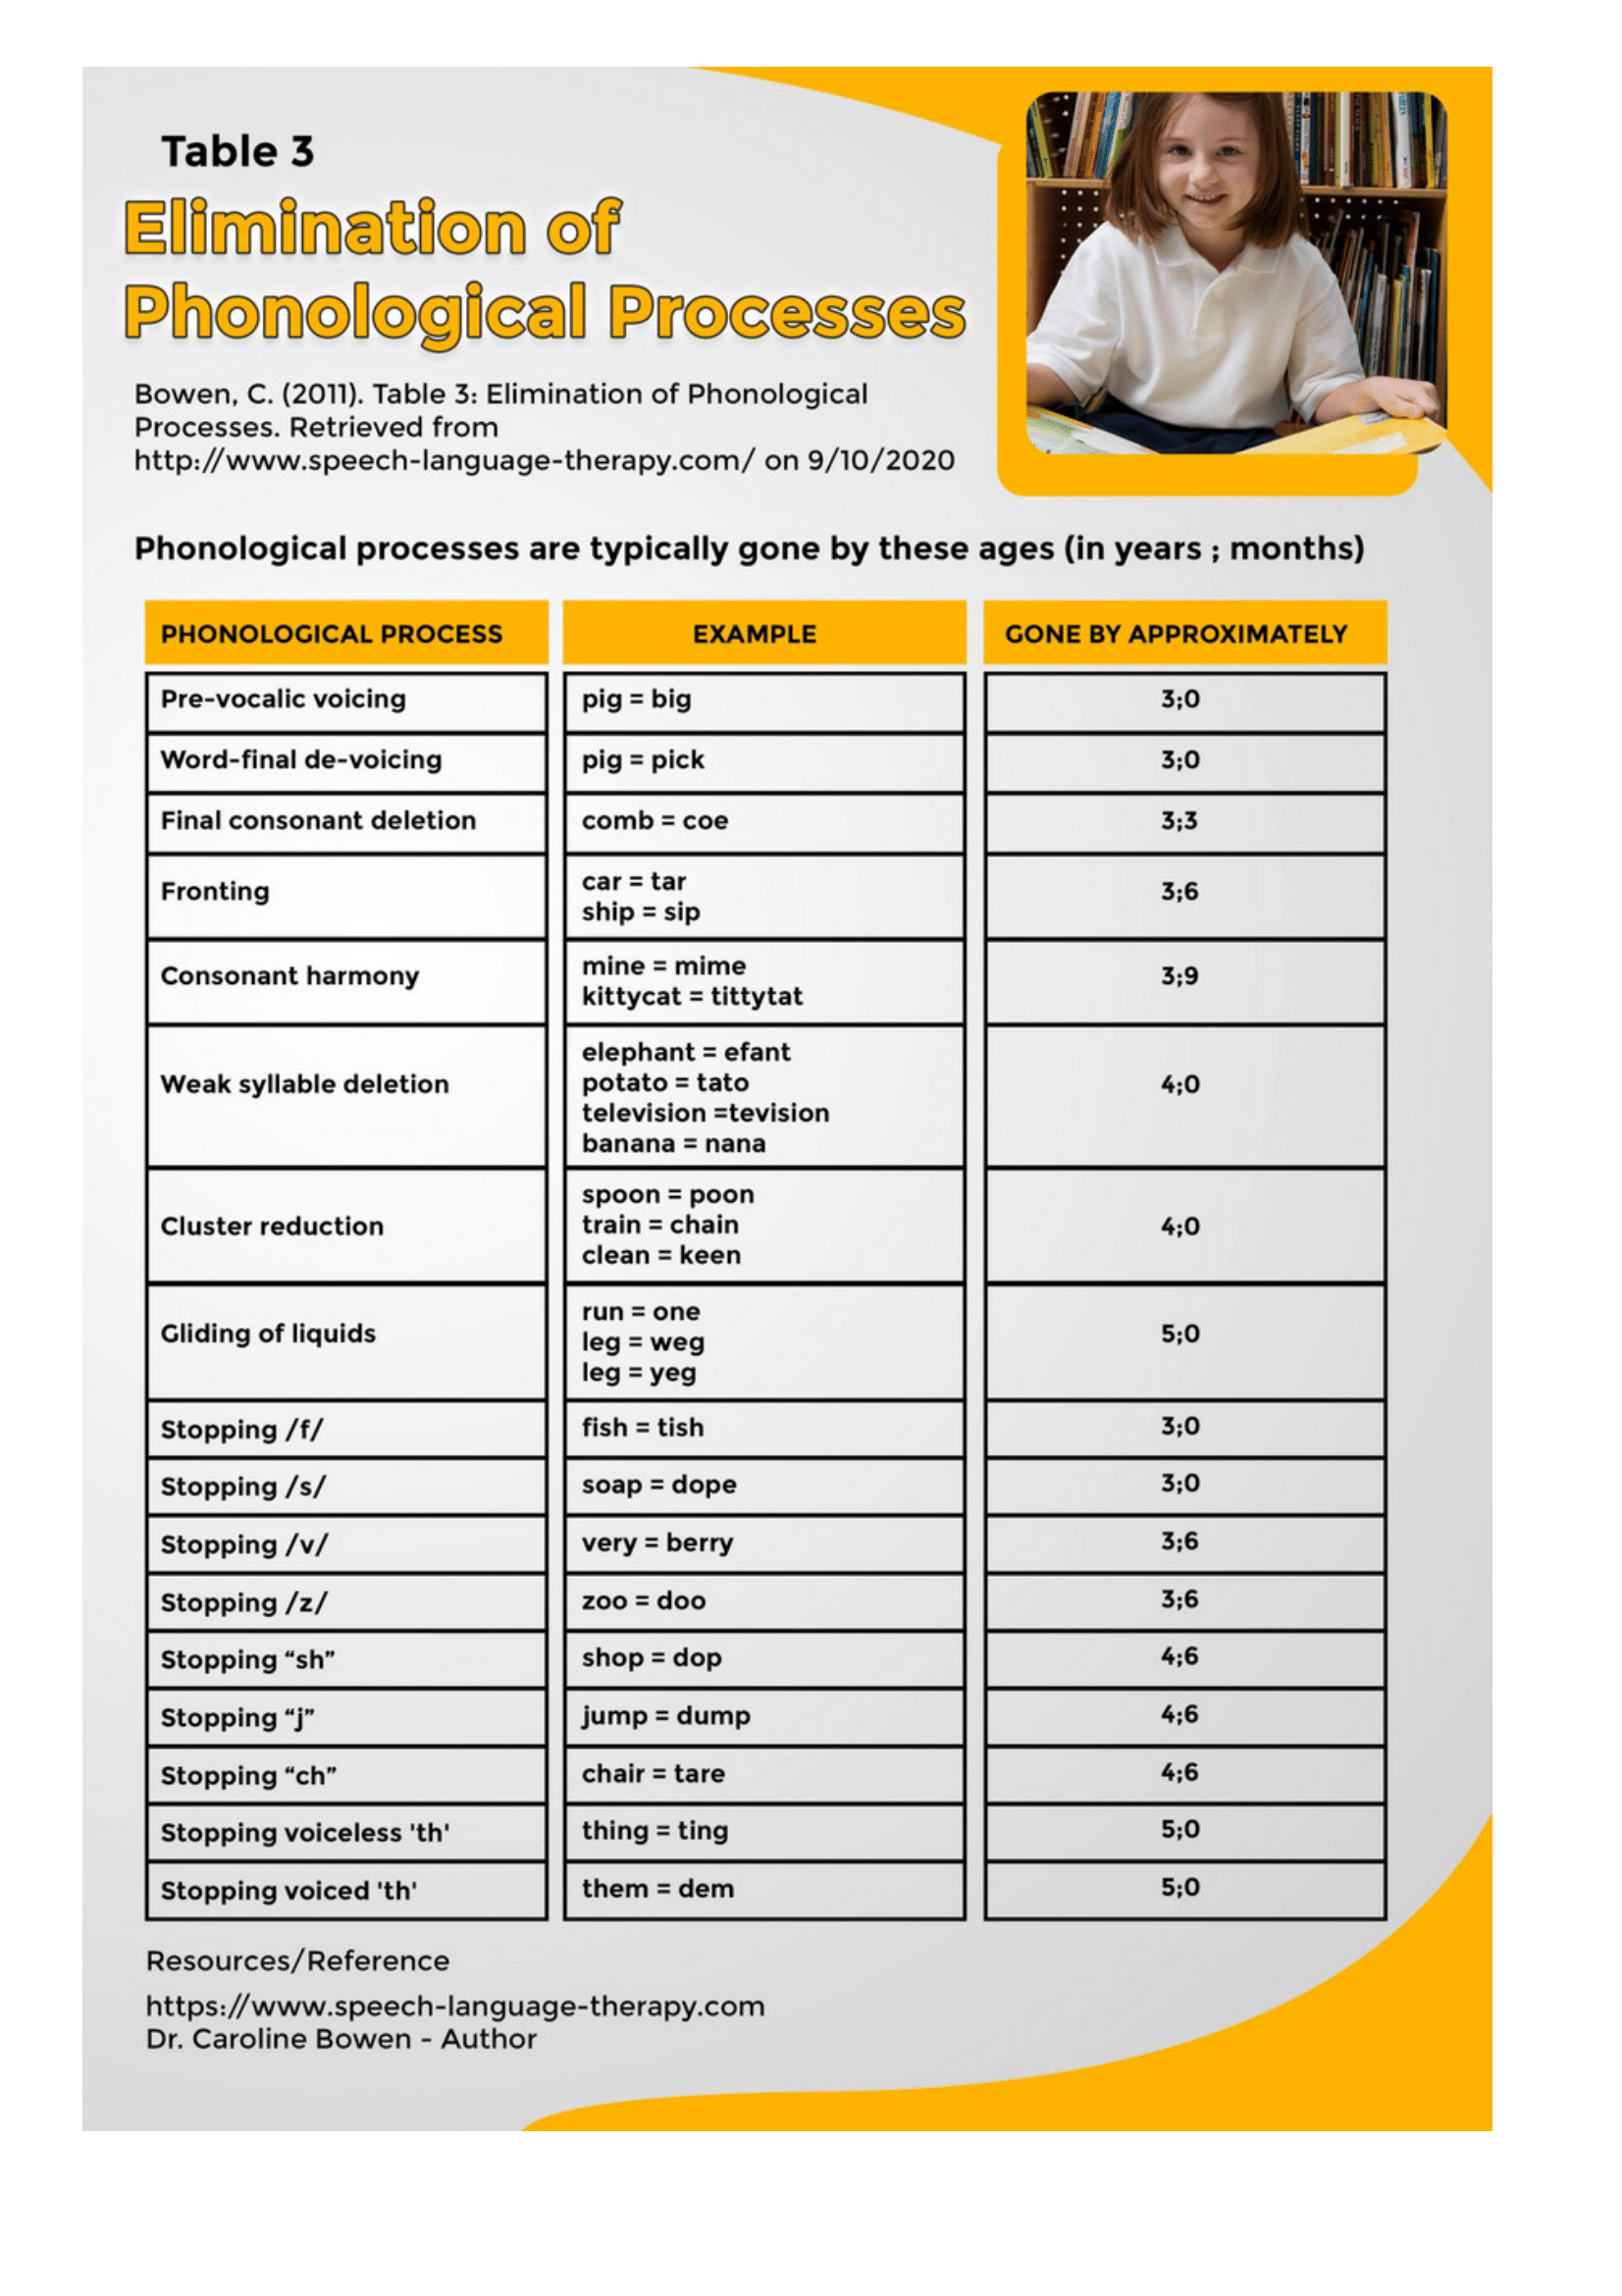
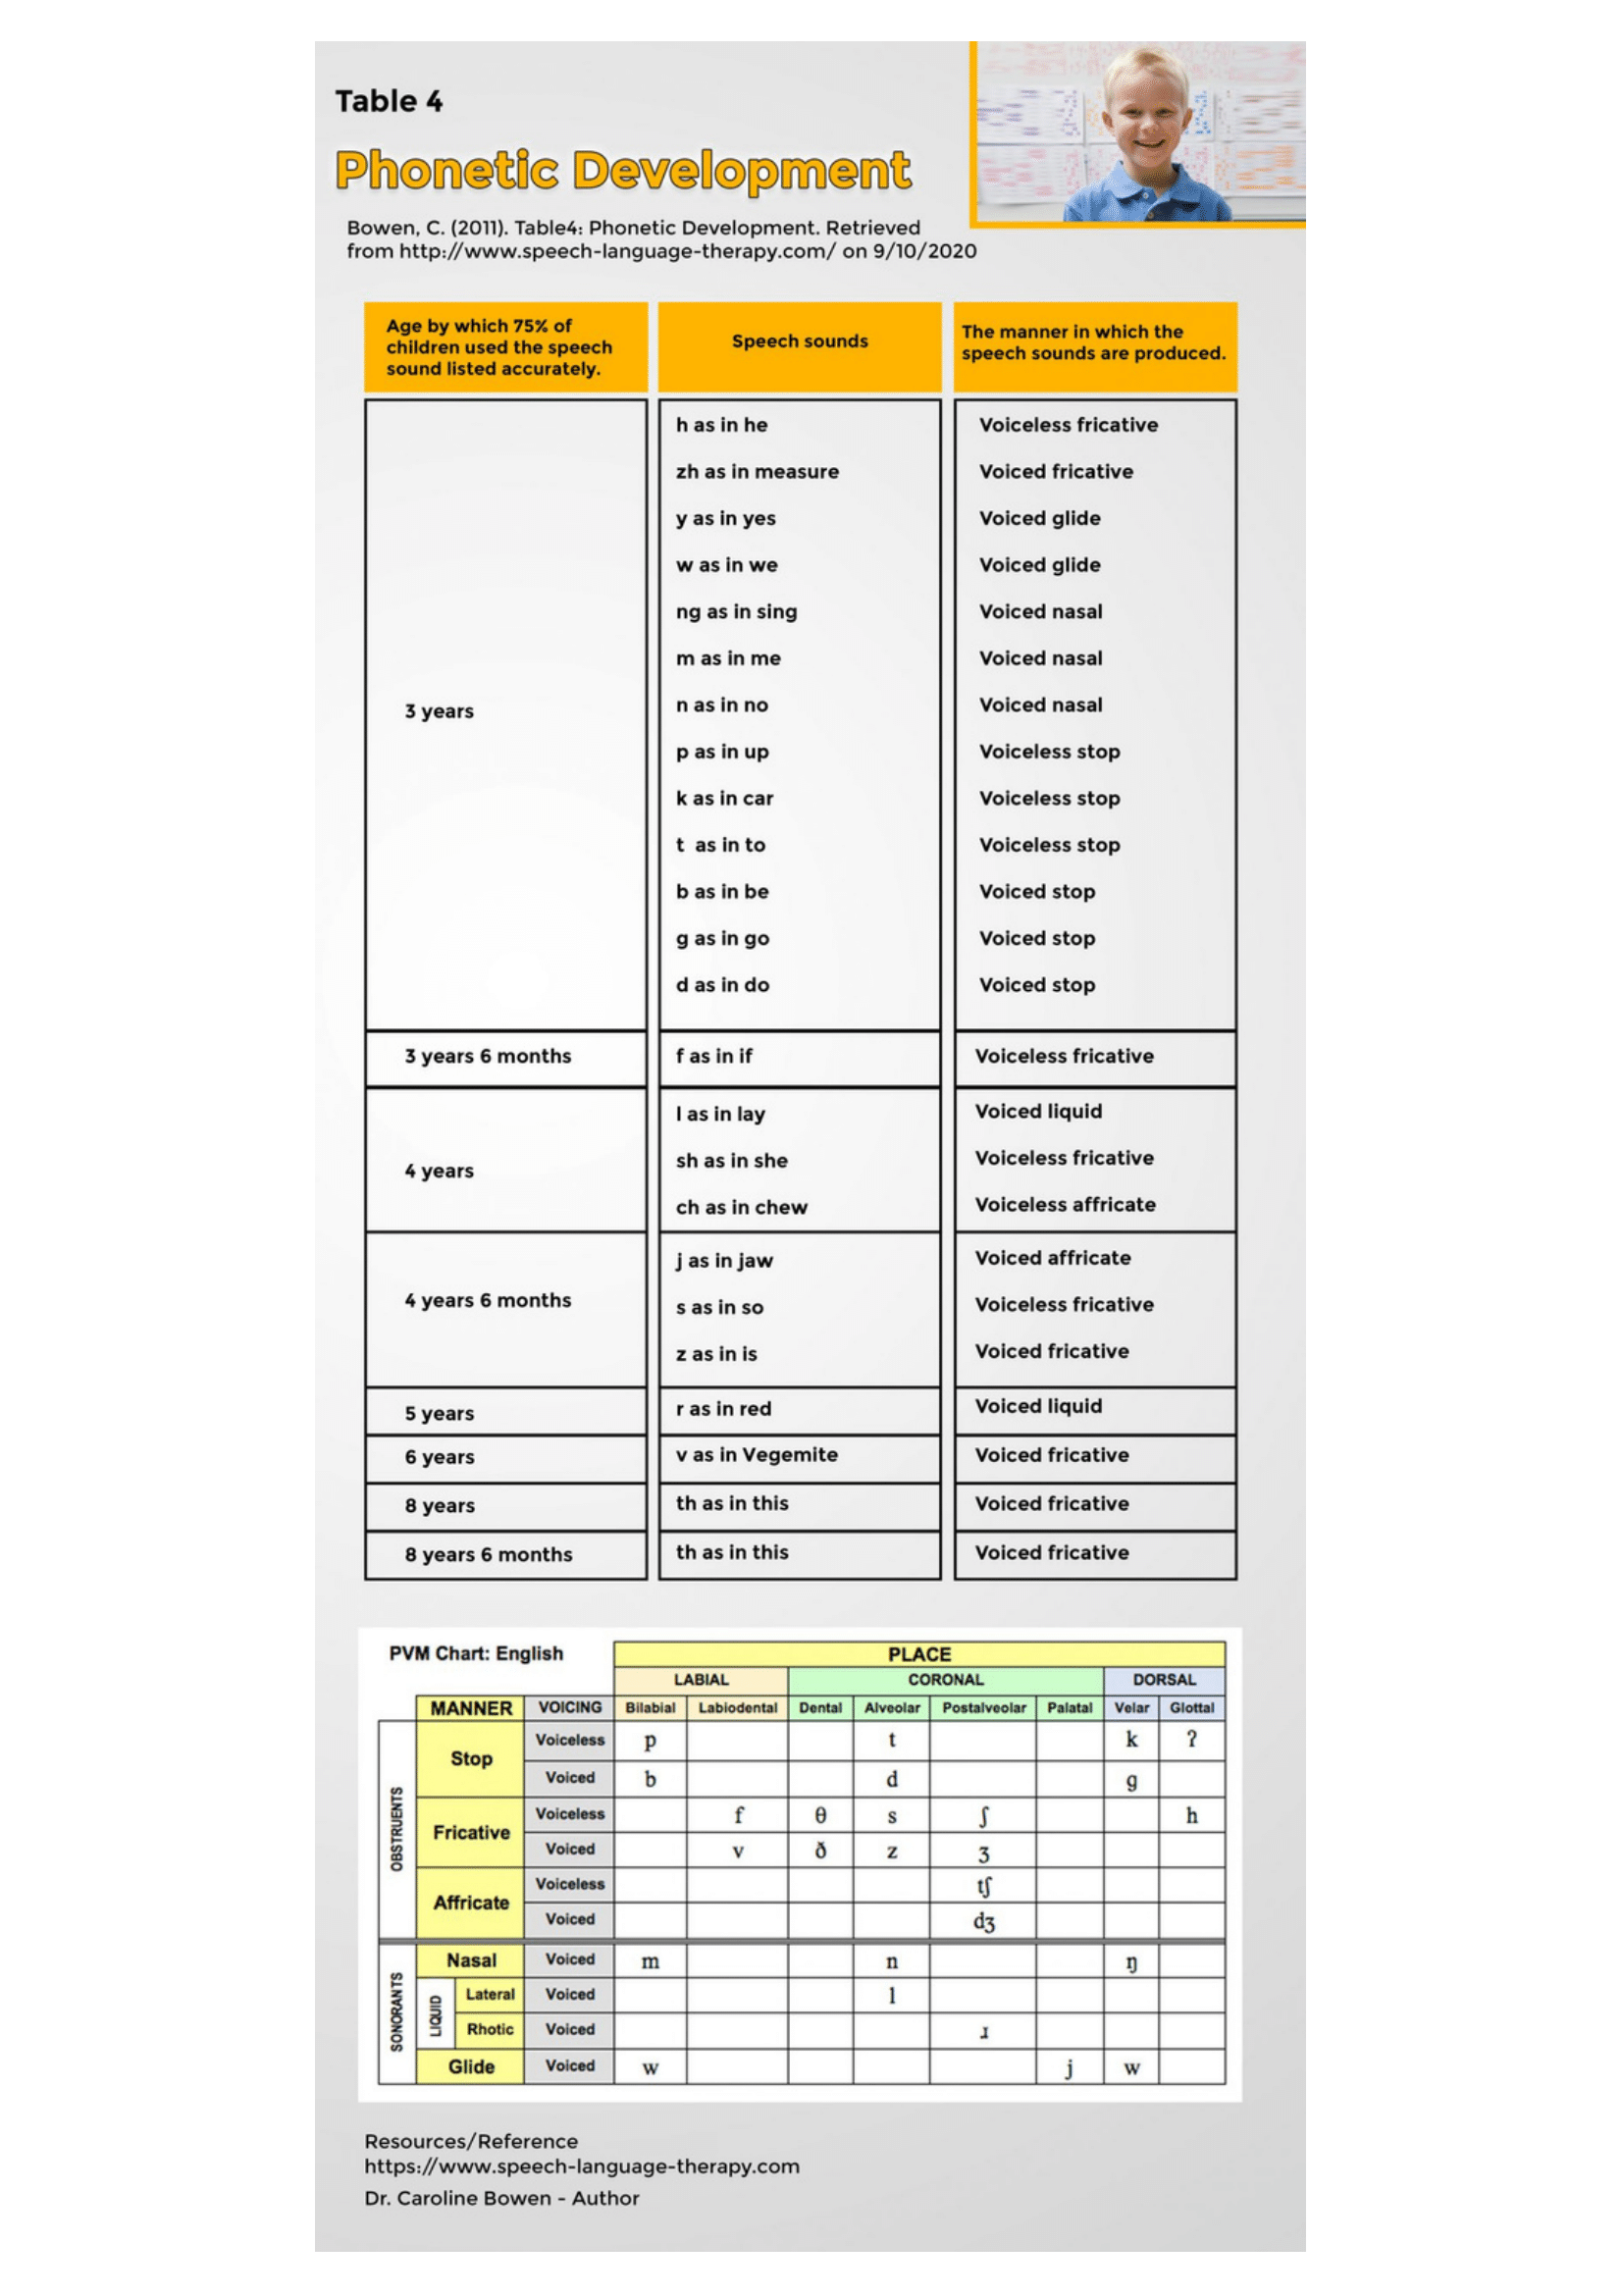
Phonological Processes
The following infographics provides a rough guide to how clearly a child should be speaking in the age-ranges. It is important to bear in mind that there is a considerable individual variation between children. If, as a parent, you are in doubt about your own child’s speech sound development or speech clarity, an assessment by a licensed speech-language pathologist/ speech and language therapist (SLP/SLT) will quickly tell you if your child is ‘on track’ and making the right combination of correct sounds and ‘errors’ for their age.
Speech Production Therapy for Children
The next steps after the assessment, if the child is deemed to need speech therapy, speech therapy starts with identifying which sound or sounds a child has trouble producing, the part of a word (beginning, middle, or ending) from which he or she is struggling to produce that sound, and, if phonological in nature, what sound or sounds he or she is omitting, substituting, etc. This analysis will also determine what type of words should be used to practice these sounds. The clinician also checks for stimulability and sound elicitation. Stimulability refers to a child’s ability to imitate a sound. If a child cannot repeat a modeled sound, the clinician will work on elicitation or teaching how to say the sound correctly. It is also possible that the child might not be ready to learn a certain sound. If this is the case, the clinician will focus on the next sound in succession and circle back to the unstimuliable sound at a later point.
Once established, the clinician can proceed with the hierarchy of speech therapy described below. Please take note that for phonological speech errors, the goals are to decrease the inappropriate phonological error(s) while increasing the correct production of the target sound(s).
- Isolation – Practicing saying a sound by itself (without adding vowels) until the child can accurately produce the sound on his or her own.
- Syllables – Adding a vowel before (initial syllable), after (final syllable), and before and after (medial syllable) the target sound. This exercise identifies in which position is easiest or hardest for the child to produce the target sound.
- Words – After learning to say the sound in syllables, the clinician uses the target sound in words. It can be the initial, medial, or final sound of the word, depending on which position needs addressing.
- Phrases / Sentences – The clinician may start with two- to three-word phrases before moving on to “rotating” sentences where only the target word changes. Kids who cannot read yet use visual cues and memorization to practice sounds.
- Stories – Practicing sounds through stories makes it easier for children to transition to conversation. Children can practice the target sound while reading aloud. For those that cannot read yet, they make up or retell stories instead.
- Conversation – The child is encouraged to practice the target sounds and words during normal conversation with few errors and little correction from the therapist. This is a good way for the clinician to gauge the child’s progress.
- Generalization – The last phase of articulation therapy focuses on generalization across all language contexts. If the child still shows difficulty generalizing the target sound, the clinician can go back to practicing words, sentences, and stories.
Common Questions
Staten Island Letters’ new chatbot (hosted on their parent company Brooklyn Letters’ website) offers quick, evidence-based answers to your developmental pediatric speech and language questions. It helps you make informed decisions without the hassle of sifting through extensive information online. It’s an excellent resource for parents, SLPs, psychologists, and other professionals seeking concise guidance on speech and language development, including understanding the crucial difference between chronological and linguistic age, speech sound acquisition, and language milestones.

MEET THE STATEN ISLAND SPEECH LANGUAGE PATHOLOGISTS WE WORK WITH WHO TRAVEL TO YOUR HOME

Sarah
M.S., CCC-SLP, SPEECH LANGUAGE PATHOLOGIST, NEW YORK STATE LICENSED CLINICIAN

Amanda
M.S., CCC-SLP, TSSLD, SPEECH-LANGUAGE PATHOLOGIST
FREE CONSULTATION!!!
Call: (347) 394-3485,
Text: (917) 426-8880
Email: statenisland@brooklynletters.com
(we respond to email right away!)